


Dengue: When fever falls, danger can rise!

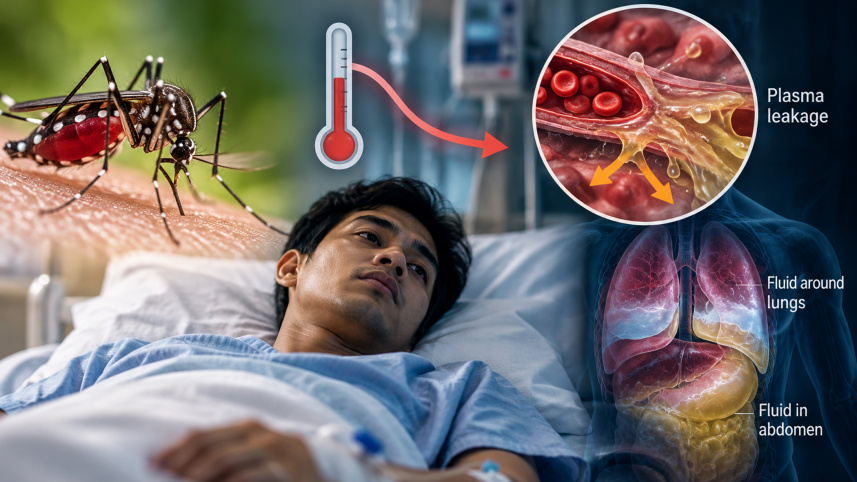
One of the most dangerous misconceptions about dengue is that once the fever disappears, the patient recovers. For many patients, that is true. But for some, a fall in temperature marks the beginning of the illness’s most dangerous period —the critical phase, when plasma leakage can develop.
Plasma is a liquid component of blood. In severe dengue, inflammation can temporarily make the walls of tiny blood vessels, or capillaries, unusually permeable. Plasma then escapes from the bloodstream into surrounding tissues and body cavities. This is known as plasma leakage.

As plasma leaves the circulation, the effective volume of blood flowing through the body falls. Blood becomes more concentrated, while fluid may accumulate around the lungs or inside the abdomen. If the leakage becomes severe, blood pressure and tissue perfusion can fall, resulting in dengue shock.
Shock means that vital organs are no longer receiving enough blood and oxygen. If this continues, the kidneys, liver, brain and heart can begin to malfunction. Severe plasma leakage can therefore lead to organ dysfunction, multi-organ failure and, in the worst cases, death.
This is why monitoring haematocrit, or HCT, is so important in dengue. Haematocrit measures the proportion of blood made up of red blood cells. When plasma leaks out of the circulation while red cells remain, the blood becomes concentrated, and the haematocrit rises.
Platelet count alone is not enough to assess dengue severity. Platelets often receive most of the attention from patients and families, but a low platelet count by itself does not tell the whole story. Doctors also need to follow haematocrit, blood pressure, pulse pressure, urine output, peripheral circulation and the patient’s overall clinical condition. A rising haematocrit, particularly with clinical deterioration, may suggest significant plasma leakage even when platelet numbers have not reached extremely low levels.
Fluid management is therefore one of the most important parts of dengue treatment.
But the answer is not simply to “give saline”. Too little fluid can be dangerous, and too much fluid can also be dangerous.
If a patient with significant plasma leakage receives inadequate fluid, the circulating blood volume may fall further, leading to shock and organ injury. On the other hand, excessive intravenous fluid can cause serious complications. The leaked fluid has not disappeared from the body. Once the blood vessels recover and stop leaking, that fluid returns to circulation. If too much saline has already been given, the patient may develop fluid overload, pulmonary oedema, breathing difficulty or cardiac complications.
The key principle is therefore the right fluid, in the right amount, at the right time, with frequent reassessment. Patients who are drinking adequately may not require intravenous fluid at all. Those with warning signs or significant plasma leakage may need carefully calculated isotonic intravenous fluids, adjusted according to blood pressure, pulse, urine output, haematocrit and clinical response.
Another worrying pattern is that some dengue patients become seriously ill just after their fever subsides — sometimes after appearing well enough to be discharged from hospital. This is usually not the dengue “coming back”. Rather, the critical phase often begins around the time of defervescence and may last for about 24 to 48 hours.
Severe abdominal pain, repeated vomiting, unusual drowsiness or restlessness, cold hands and feet, breathing difficulty, bleeding, dizziness or reduced urine output after the fever settles should therefore prompt urgent medical assessment.
In dengue, a falling temperature can sometimes signal rising danger. Understanding plasma leakage and managing fluids correctly during this narrow critical window can make the difference between uncomplicated recovery and life-threatening shock.
E-mail: tareq.salahuddin@thedailystar.net
 For all latest news, follow The Daily Star's Google News channel.
Comments